logo
0

Infant Milk Allergy: Signs, Diagnosis & Formula Options

Learn the signs of infant milk allergy, how doctors diagnose CMPA, which hypoallergenic formulas may help, and when to seek medical care.

article image

Dr.Bhanu Prakash

Feeding a newborn is stressful enough without the worry that something in the formula or your diet could be harming your baby. Infant milk allergy, medically called Cow's milk protein allergy (CMPA), is one of the most common food allergies in infancy and is particularly common during the first year of life. Knowing the signs early, getting a proper diagnosis, and choosing the right formula can make a meaningful difference to your baby's comfort, growth, and overall well-being.

What Is Infant Milk Allergy?

Cow's milk protein allergy in babies is an immune system reaction to one or more proteins found in cow's milk, most commonly casein and whey. The immune system mistakenly identifies these proteins as harmful and mounts a response, triggering symptoms that range from mild to severe.

There are two main types:

  • IgE-mediated: Symptoms typically develop within minutes to 2 hours after exposure and may include hives, swelling, vomiting, wheezing, or other acute allergic symptoms.
  • Non-IgE-mediated: Symptoms are delayed and may develop several hours to days after exposure, often involving the gastrointestinal tract.

Many parents confuse milk allergy with lactose intolerance, but these are very different conditions. Lactose intolerance is not an immune reaction. It happens when the body lacks enough of the enzyme lactase to digest lactose, the sugar in milk, causing gas, bloating, and loose stools.

Primary lactose intolerance is uncommon in young infants, although temporary secondary lactose intolerance can occur, particularly after intestinal illness. CMPA, by contrast, involves the immune system reacting to milk proteins and can produce more serious symptoms. The two need different management, which is exactly why a proper diagnosis matters.

Signs and Symptoms to Watch For

Signs of milk allergy in infants can appear across several body systems, and the pattern varies from baby to baby.

Digestive symptoms are the most common:

  • Frequent vomiting or posseting beyond typical newborn spitting up.
  • Diarrhoea, sometimes with blood or mucus in the stool.
  • Colic-like crying, especially after feeds.
  • Persistent constipation or significant changes in bowel habits.
  • Visible discomfort during or after feeds, such as drawing up of legs or back arching.

Skin reactions are also frequently seen:

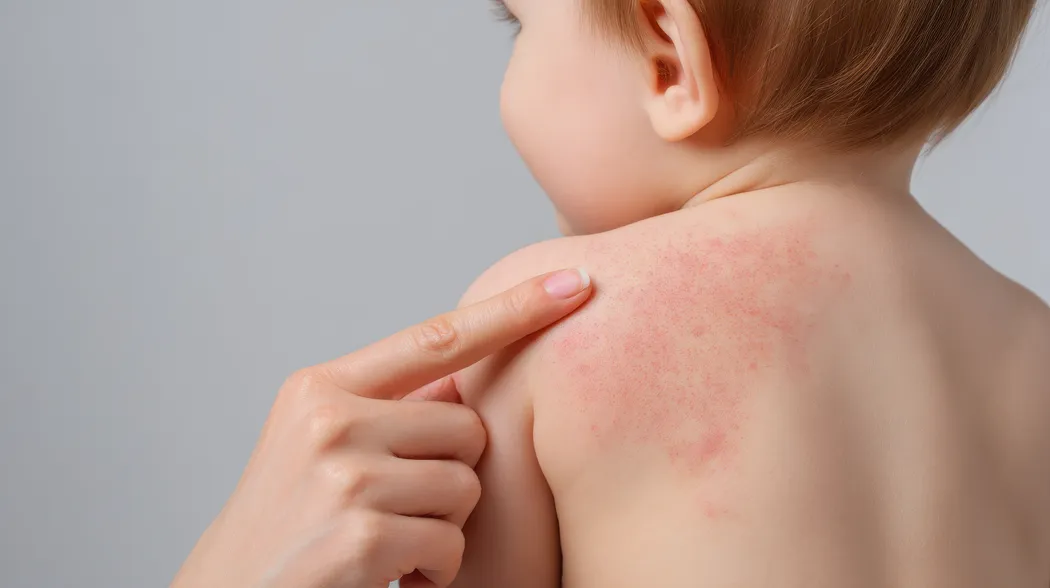
  • Eczema or dry, itchy patches, particularly on the face, neck, or behind the knees.
  • Hives (raised, red, itchy welts) appearing shortly after a feed.
  • Swelling around the mouth or eyes.

Respiratory signs sometimes accompany the above:

  • A persistently runny or blocked nose with no obvious infection.
  • Wheezing or a recurring cough.

Seek emergency help immediately if your baby develops sudden swelling of the lips or throat, difficulty breathing, goes pale or floppy, or loses consciousness after feeding. These can be signs of anaphylaxis. Report adverse events to your healthcare provider or the relevant regulatory authority.

How Doctors Diagnose Milk Allergy in Infants

No single test gives a definitive answer, and self-diagnosis is not reliable. A paediatrician or paediatric allergist will typically use a combination of approaches.

A detailed feeding history is usually the starting point. Your doctor will ask about symptoms, their timing, and what your baby is being fed (or what you eat if you are breastfeeding).

  • Elimination Trial: For a breastfed infant with symptoms strongly suggestive of CMPA, a paediatrician may recommend a 2-4 week maternal cow's-milk elimination trial, followed by planned reintroduction to help confirm the diagnosis. For formula-fed babies, a switch to a hypoallergenic infant formula may be trialled under medical guidance. Reintroduction under supervision can help confirm the diagnosis if symptoms return.
  • Skin Prick Testing: Skin prick testing can support the evaluation of suspected IgE-mediated milk allergy, but it cannot diagnose CMPA on its own. Its usefulness depends on the clinical history, and it is generally not helpful for non-IgE-mediated CMPA.
  • Specific IgE Blood Tests: These blood tests measure antibodies to milk proteins and may be ordered alongside or instead of skin prick testing.
  • Endoscopy or Colonoscopy: These procedures are rarely needed but may be considered when there is blood in the stool or severe gastrointestinal symptoms that do not improve with initial management.

Never switch formulas or remove foods from your diet without talking to a doctor first. Unnecessary formula changes can mask the real problem or create nutritional gaps.

Specialized Formula Options: From Extensively Hydrolyzed to Amino Acid-Based

When a formula-fed baby is diagnosed with infant milk allergy, doctors generally recommend moving to a hypoallergenic formula for infants. These fall into a hierarchy based on how thoroughly the milk proteins have been broken down.

Formula Type

How It Works

Suitable For

Extensively hydrolyzed (eHF)

Proteins broken into very small fragments

Mild to moderate CMPA, first-line choice

Amino acid-based (elemental)

No proteins at all, only free amino acids

Severe CMPA, failed eHF, multiple food allergies

Soy-based

Plant-derived protein

Not recommended routinely in infancy

Partially hydrolyzed

Mildly broken-down proteins

Not suitable for managing CMPA

For formula-fed infants with suspected or confirmed mild to moderate CMPA, an extensively hydrolysed formula (eHF) is generally the preferred first-line option.

Amino acid-based formula (AAF) contains free amino acids rather than intact milk proteins or peptides and has very low allergenicity. It is generally reserved for severe CMPA, including cases involving anaphylaxis, significant nutritional compromise or faltering growth, multiple food allergies, or persistent symptoms despite an appropriate extensively hydrolysed formula.

Partially hydrolyzed formulas are marketed for comfort or colic but do not offer adequate protection for a baby with a true allergy. Soy formula is not usually the first-choice option for CMPA, and some infants with CMPA also have soy allergy.

All specialized formulas should be started on your paediatrician's advice and monitored for growth. For broader guidance on caring for a young baby from the earliest weeks, the newborn care essentials guide covers useful practical information.

Contraindications and Precautions

Amino acid-based and extensively hydrolyzed formulas are not appropriate in every situation. A doctor must assess your baby before any formula switch.

These specialized formulas should not be used:

  • As a substitute for medical evaluation. Baby formula allergy symptoms can overlap with other conditions, including reflux, infections, and metabolic disorders.
  • When a baby has a known allergy or sensitivity to a specific ingredient in that particular formula product.
  • Instead of, not alongside, ongoing medical monitoring. Growth and nutritional adequacy must be checked regularly.

Parents should not use oat, almond, rice or other plant-based drinks as substitutes for breast milk or infant formula during the first 12 months. These drinks are not appropriate as the main milk feed for infants.
When to See a Pediatrician or Allergist

See your doctor promptly if your baby has any of the digestive, skin, or respiratory symptoms described above, especially if they are recurrent or linked to feeding.

Go to an emergency department or call emergency services immediately if your baby shows signs of a severe allergic reaction: sudden swelling of the face or throat, difficulty breathing, or sudden limpness.

Do not attempt to diagnose infant milk allergy at home or switch formulas based on online guidance alone. A paediatrician-led assessment, and where needed a referral to a paediatric allergist, is the safest path. This is especially important because early, accurate diagnosis protects your baby's nutrition and prevents unnecessary dietary restrictions.

Conclusion

Infant milk allergy, or cow's milk protein allergy (CMPA), can cause digestive, skin, and respiratory symptoms in babies and may sometimes require specialised formula. Because its symptoms can overlap with other infant conditions, proper diagnosis by a paediatrician is essential rather than making an independent formula switch.

For formula-fed babies with confirmed CMPA, extensively hydrolysed formulas are generally considered first-line options, while amino acid-based formulas may be recommended for severe cases or when symptoms do not improve. Partially hydrolysed formulas and plant-based drinks should not be used as substitutes for medically appropriate allergy management. With early diagnosis, appropriate nutritional support, and regular medical monitoring, most babies can be kept comfortable while their nutritional needs and growth are protected.

FAQS

Can a breastfed baby have a milk allergy?

Yes. Cow's milk proteins from the mother's diet can pass into breast milk in small amounts and trigger symptoms in a sensitized baby. If this is suspected, a paediatrician will usually recommend a maternal dairy elimination trial.

Does milk allergy in babies go away?

Many children eventually develop tolerance to cow's milk, but the timing varies considerably according to the type and severity of allergy. Your paediatrician should determine when and how milk can be reintroduced. Your doctor will periodically supervise a reintroduction challenge to check whether tolerance has developed.

What is the difference between milk allergy and milk intolerance?

Milk allergy is an immune system reaction to milk proteins and can cause symptoms across the gut, skin, and airways. Milk intolerance (usually lactose intolerance) is a digestive issue caused by insufficient lactase enzyme and produces gas, bloating, and loose stools but does not involve the immune system.

How long does it take to see improvement after a formula change?

Symptoms often improve during the first few weeks after an appropriate elimination diet or hypoallergenic formula is started, although the timing varies by symptom and by type of CMPA. Your paediatrician should reassess your baby if symptoms persist. If there is no improvement after four weeks on the new formula, go back to your paediatrician.

Can milk allergy in infants be prevented?

Current evidence does not support any single strategy for guaranteed prevention. WHO and UNICEF recommend exclusive breastfeeding for the first six months of life, followed by appropriate complementary foods while breastfeeding continues.

Apollo 247 Floating Action Button